PT-141 (Bremelanotide) vs Setmelanotide
The distinction that mattersBoth melanocortin agonists. Setmelanotide targets MC4R for genetic obesity and is dosed daily; PT-141 targets MC3R/MC4R for sexual desire and is dosed on demand.
| PT-141 (Bremelanotide) FDA Approved | Setmelanotide FDA Approved | |
|---|---|---|
| Evidence rating |
5/5 Very strong
Evidence rating 5 out of 5: Very strong
|
5/5 Very strong
Evidence rating 5 out of 5: Very strong
|
| Regulatory status | FDA-approved (2019) for acquired, generalized hypoactive sexual desire disorder in premenopausal women | FDA-approved for obesity due to POMC, PCSK1 or LEPR deficiency, and for Bardet-Biedl syndrome |
| Category | Sexual Health & Melanocortin | Metabolic & Weight |
| Drug class | Melanocortin receptor agonist (MC3R/MC4R) — cyclic heptapeptide | Melanocortin-4 receptor (MC4R) agonist — cyclic octapeptide |
| Route | Subcutaneous autoinjector, as needed | Subcutaneous, once daily |
| Half-life | ~2.7 hours | ~11 hours |
| Sequence length | 7 residues | 8 residues |
| Molecular weight | 1,025.2 Da | 1,117.3 Da |
| Studied in | RECONNECT phase 3 trials in premenopausal women with HSDD; earlier studies in erectile dysfunction including an intranasal formulation that was discontinued over blood-pressure effects. | Pivotal open-label trials in POMC/LEPR deficiency and a randomized trial in Bardet-Biedl syndrome. |
| Who should avoid it |
|
|
| Legal status | Prescription drug for its labelled indication. "Research grade" PT-141 sold online is unapproved. | Prescription drug restricted to labelled genetic indications. |
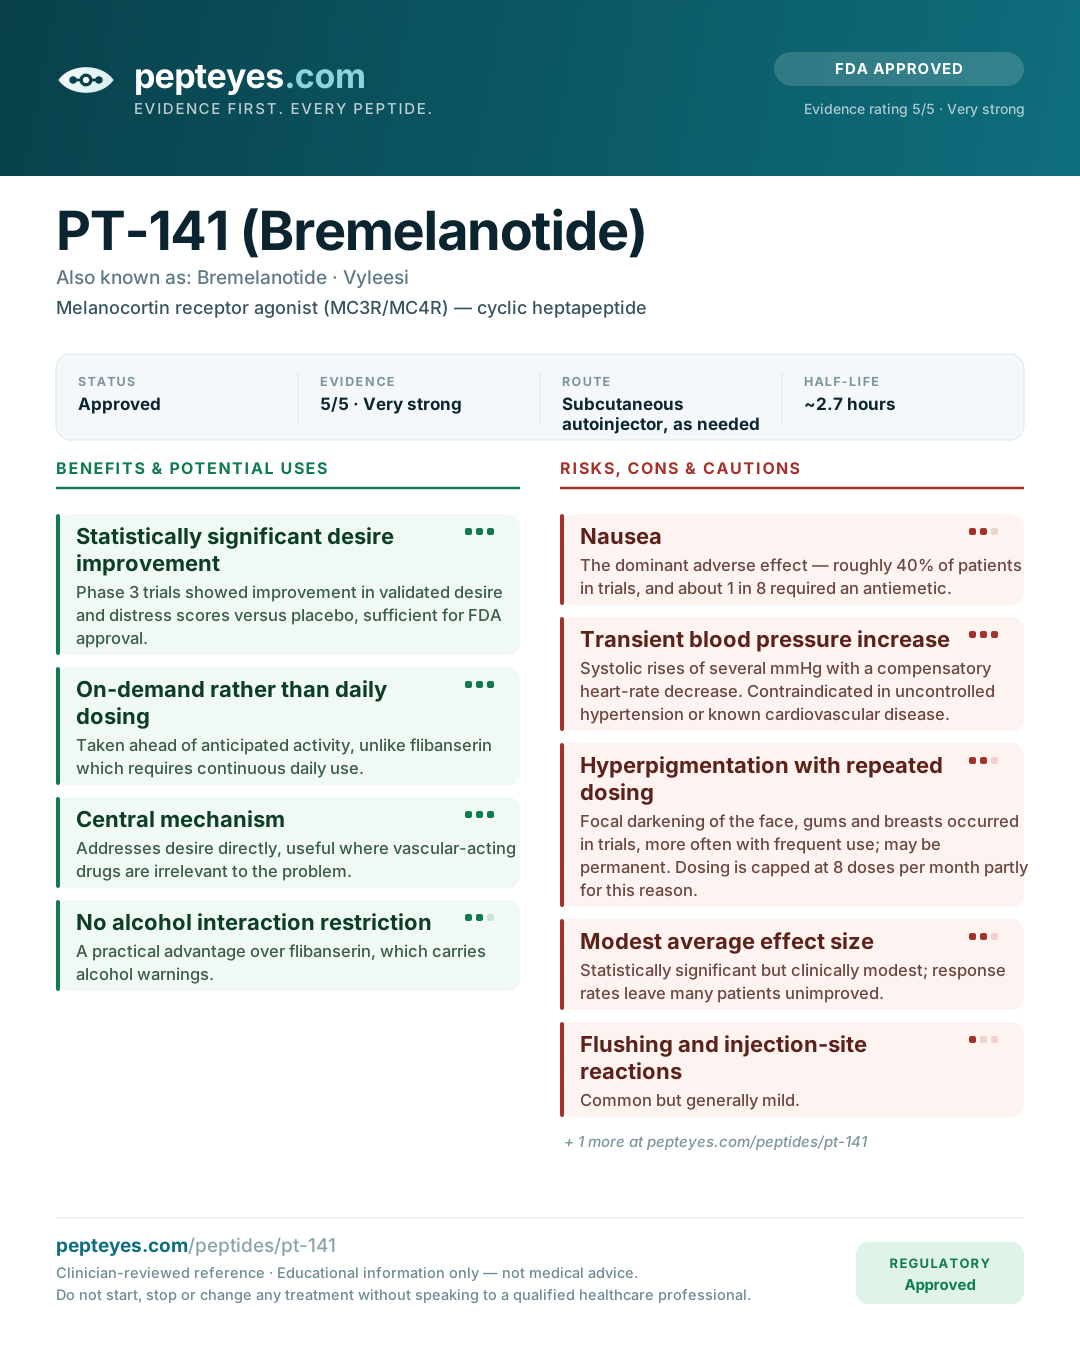
Benefits — PT-141 (Bremelanotide)
- Statistically significant desire improvement
Phase 3 trials showed improvement in validated desire and distress scores versus placebo, sufficient for FDA approval.
- On-demand rather than daily dosing
Taken ahead of anticipated activity, unlike flibanserin which requires continuous daily use.
- Central mechanism
Addresses desire directly, useful where vascular-acting drugs are irrelevant to the problem.
- No alcohol interaction restriction
A practical advantage over flibanserin, which carries alcohol warnings.
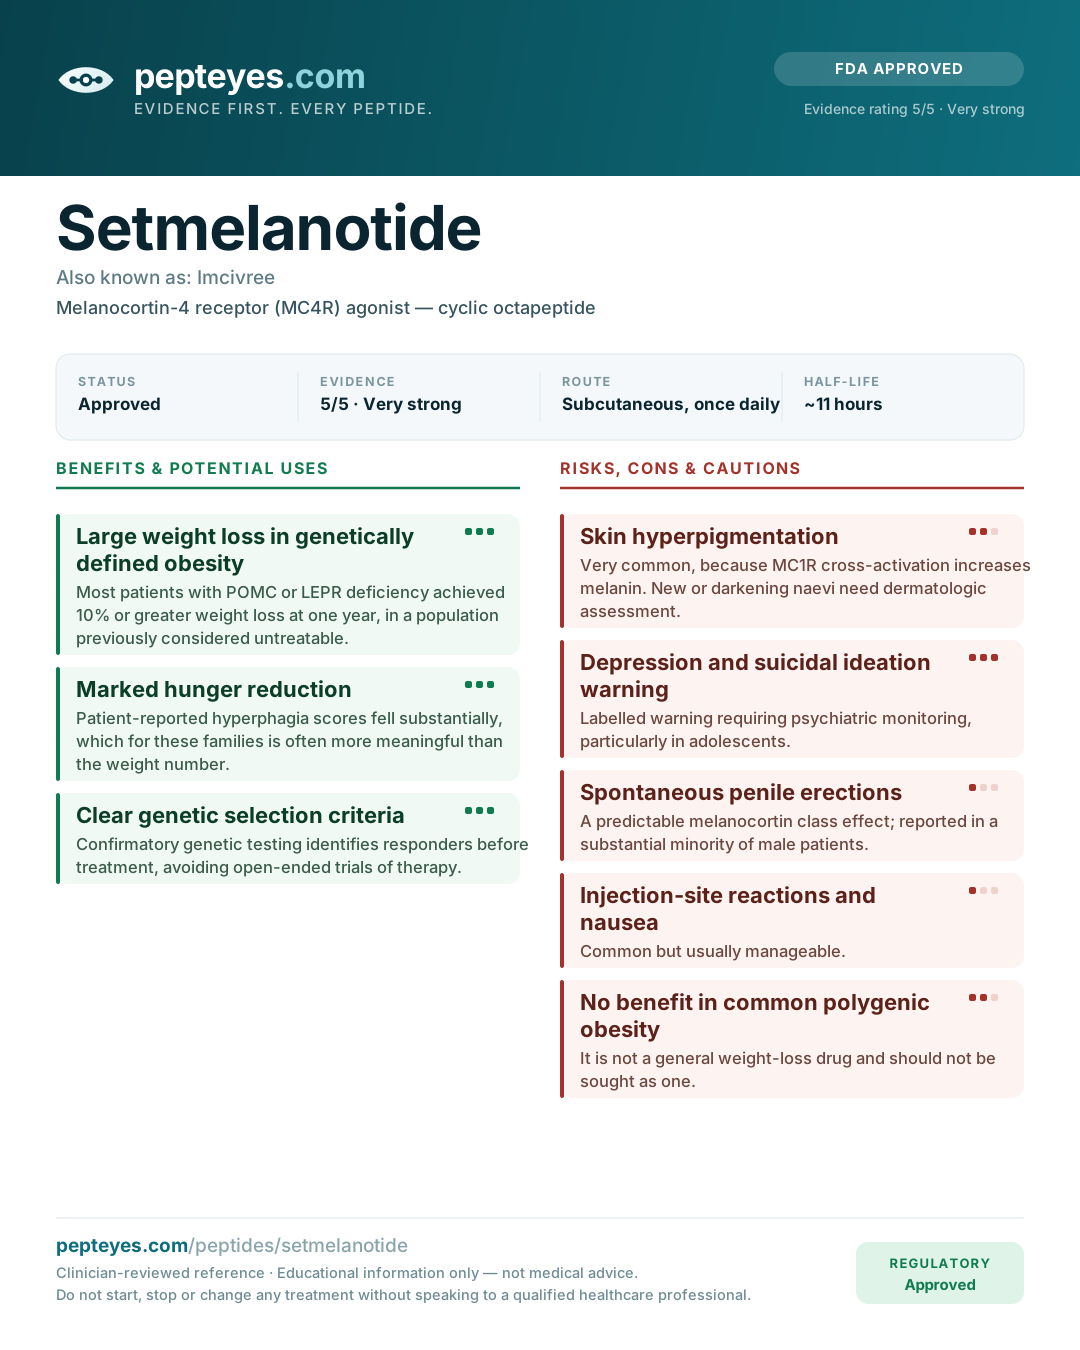
Benefits — Setmelanotide
- Large weight loss in genetically defined obesity
Most patients with POMC or LEPR deficiency achieved 10% or greater weight loss at one year, in a population previously considered untreatable.
- Marked hunger reduction
Patient-reported hyperphagia scores fell substantially, which for these families is often more meaningful than the weight number.
- Clear genetic selection criteria
Confirmatory genetic testing identifies responders before treatment, avoiding open-ended trials of therapy.
Risks & cons — PT-141 (Bremelanotide)
- Nausea
The dominant adverse effect — roughly 40% of patients in trials, and about 1 in 8 required an antiemetic.
- Transient blood pressure increase
Systolic rises of several mmHg with a compensatory heart-rate decrease. Contraindicated in uncontrolled hypertension or known cardiovascular disease.
- Hyperpigmentation with repeated dosing
Focal darkening of the face, gums and breasts occurred in trials, more often with frequent use; may be permanent. Dosing is capped at 8 doses per month partly for this reason.
- Modest average effect size
Statistically significant but clinically modest; response rates leave many patients unimproved.
- Flushing and injection-site reactions
Common but generally mild.
Risks & cons — Setmelanotide
- Skin hyperpigmentation
Very common, because MC1R cross-activation increases melanin. New or darkening naevi need dermatologic assessment.
- Depression and suicidal ideation warning
Labelled warning requiring psychiatric monitoring, particularly in adolescents.
- Spontaneous penile erections
A predictable melanocortin class effect; reported in a substantial minority of male patients.
- Injection-site reactions and nausea
Common but usually manageable.
- No benefit in common polygenic obesity
It is not a general weight-loss drug and should not be sought as one.
A comparison is not a recommendation. Neither column is being suggested for you. Which — if either — is appropriate depends on your diagnosis, history and medications, and that is a conversation for a qualified clinician.