Ipamorelin vs MK-677 (Ibutamoren)
Injectable selective secretagogue versus the oral one with a heart failure signal.
The distinction that mattersSame receptor, but MK-677 is an oral non-peptide with sustained rather than pulsatile action — and the only one of the two with a long-term human trial, which found a heart failure signal.
These are not equivalent in evidence MK-677 (Ibutamoren) is rated 3/5 and Ipamorelin is rated 2/5 — a gap of 1 level on our scale. Similar marketing does not mean similar proof.
| Ipamorelin Research Use Only | MK-677 (Ibutamoren) Not a Peptide | |
|---|---|---|
| Evidence rating |
2/5 Limited
Evidence rating 2 out of 5: Limited
|
3/5 Moderate
Evidence rating 3 out of 5: Moderate
|
| Regulatory status | Investigational only, and not approved anywhere. Two phase 2 trials in postoperative recovery of gastrointestinal function were completed without demonstrating benefit, after which development was abandoned. Widely supplied through wellness clinics and research-chemical sellers, which is not the same as being lawfully available. | Not a peptide. Investigational drug; development discontinued. Not approved. Prohibited in sport. |
| Category | Growth Hormone Axis | Growth Hormone Axis |
| Drug class | Selective ghrelin receptor (GHS-R1a) agonist — pentapeptide | Non-peptide, orally active ghrelin receptor agonist — listed here because it is universally marketed alongside peptides |
| Route | Subcutaneous (research) | Oral, once daily |
| Half-life | ~2 hours | ~4-6 h in beagles; no published human half-life. A single oral dose keeps GH and IGF-1 raised for about 24 hours. |
| Sequence length | 5 residues | Not a peptide |
| Molecular weight | 711.9 Da | 528.7 Da |
| Studied in | Healthy-volunteer intravenous pharmacokinetics and GH response (1999); two completed phase 2 trials of postoperative recovery of gastrointestinal function, neither positive, after which development stopped; rodent studies of gut motility, longitudinal bone growth and bone mineral content. | Multiple phase 2 trials including elderly hip-fracture recovery, sarcopenia, GH deficiency, and a 2-year trial in healthy older adults. |
| Who should avoid it |
|
|
| Legal status | Not approved by the FDA, the EMA or any comparable regulator for any indication, and not eligible for lawful pharmacy compounding in the United States. Selling it for human use is unlawful. “Research use only” or “not for human consumption” labelling is a seller’s disclaimer about intended use, not a regulatory category, and confers nothing on the buyer. The compounding position is disputed and moving; the dated record is on this page. | Unapproved investigational drug. Not lawful as a dietary supplement in the US. WADA-prohibited. |
Benefits — Ipamorelin
- Selective GH release
Clean pharmacology: GH rises without the cortisol and prolactin spikes seen with hexarelin or GHRP-6.
- Minimal appetite stimulation
Unlike GHRP-6, it does not produce the intense hunger that makes those peptides impractical.
- Good short-term tolerability
Trial safety data in the ileus program were reassuring over short exposures.
- Synergy with GHRH analogs
The two mechanisms combine to produce a larger pulse than either alone.
- A measurable, reproducible GH pulse in healthy humans
A 1999 dose-escalation study in healthy male volunteers (eight men at each of five ascending intravenous infusion rates) found dose-proportional pharmacokinetics, a terminal half-life near two hours, and a single episode of GH release peaking around 40 minutes and decaying to negligible concentrations at every exposure tested. This is the clearest human evidence the compound does what it says — and it is evidence about a hormone measurement, not about anything a person would notice.
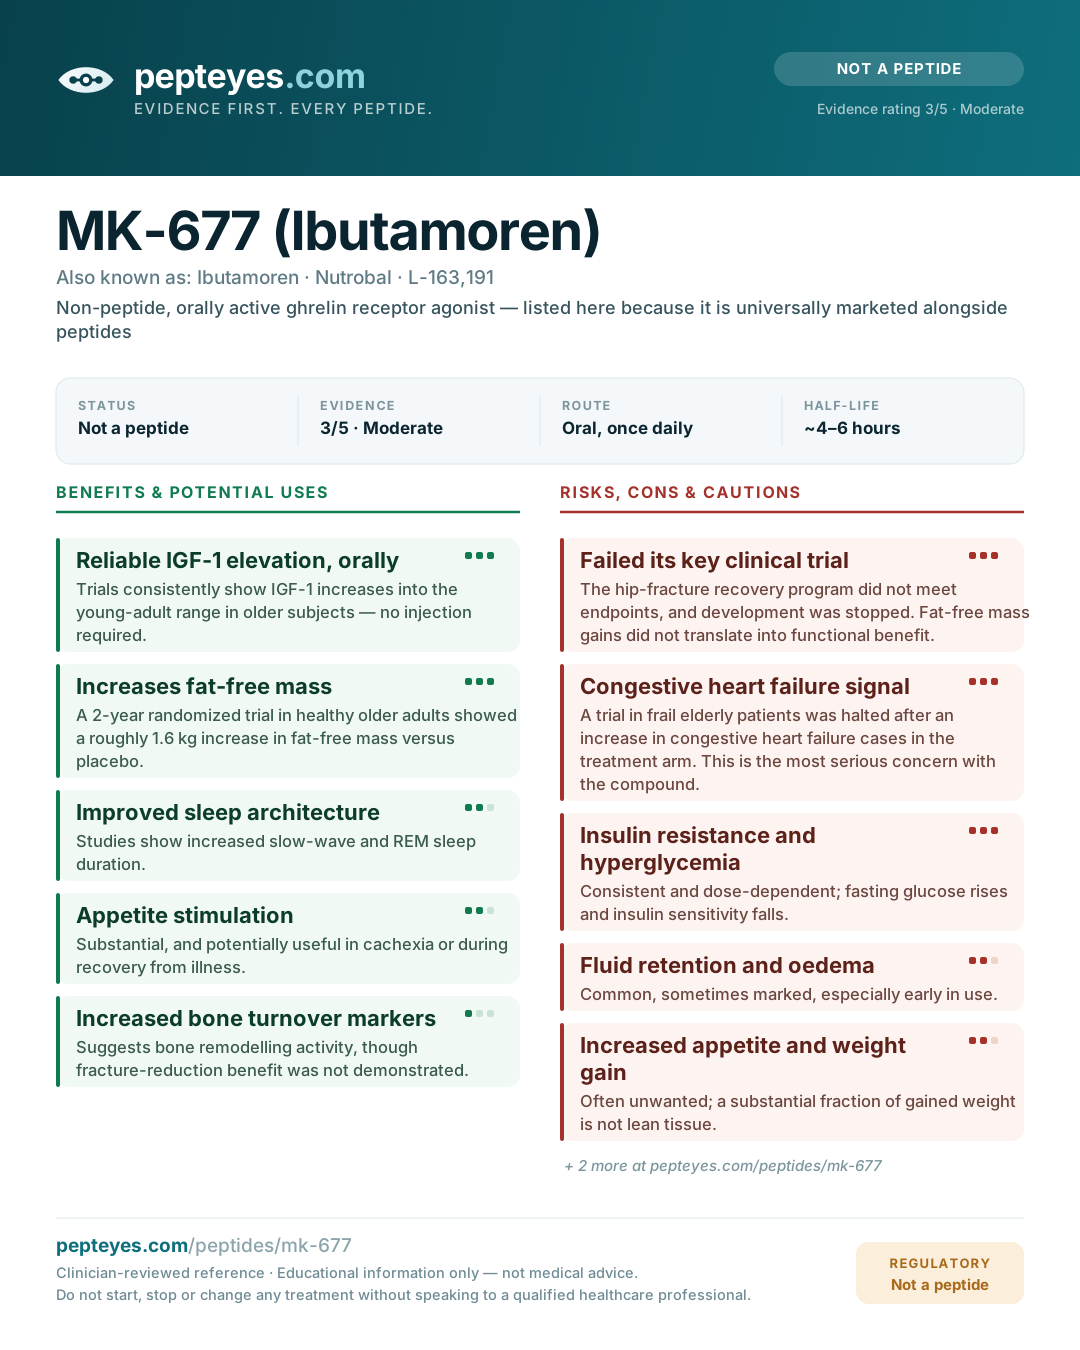
Benefits — MK-677 (Ibutamoren)
- Reliable IGF-1 elevation, orally
Trials consistently show IGF-1 increases into the young-adult range in older subjects — no injection required.
- Increases fat-free mass
A 2-year randomized trial in healthy older adults showed a roughly 1.6 kg increase in fat-free mass versus placebo.
- Improved sleep architecture
Studies show increased slow-wave and REM sleep duration.
- Appetite stimulation
Substantial, and potentially useful in cachexia or during recovery from illness.
- Increased bone turnover markers
Suggests bone remodelling activity, though fracture-reduction benefit was not demonstrated.
Risks & cons — Ipamorelin
- No proven clinical benefit
The trials that were run targeted gut motility and were discontinued. Body-composition and recovery claims are untested.
- Unapproved and unregulated
Available only through compounding or grey-market suppliers, with corresponding quality uncertainty.
- Glucose and insulin effects
Raising the GH axis can worsen insulin sensitivity over time.
- Receptor desensitisation
Continuous ghrelin-receptor stimulation blunts the response; effects diminish with sustained use.
- Head/injection-site reactions
Headache, flushing and local reactions are reported.
Risks & cons — MK-677 (Ibutamoren)
- Failed its key clinical trial
The hip-fracture recovery program did not meet endpoints, and development was stopped. Fat-free mass gains did not translate into functional benefit.
- Congestive heart failure signal
A trial in frail elderly patients was halted after an increase in congestive heart failure cases in the treatment arm. This is the most serious concern with the compound.
- Insulin resistance and hyperglycemia
Consistent and dose-dependent; fasting glucose rises and insulin sensitivity falls.
- Fluid retention and oedema
Common, sometimes marked, especially early in use.
- Increased appetite and weight gain
Often unwanted; a substantial fraction of gained weight is not lean tissue.

A comparison is not a recommendation. Neither column is being suggested for you. Which — if either — is appropriate depends on your diagnosis, history and medications, and that is a conversation for a qualified clinician.