CJC-1295 vs Somatropin (recombinant hGH)
The distinction that mattersMarketing often implies these are equivalent. CJC-1295 has phase 1 data only; somatropin has decades of trials and a specific federal law governing its distribution.
These are not equivalent in evidence Somatropin (recombinant hGH) is rated 5/5 and CJC-1295 is rated 2/5 — a gap of 3 levels on our scale. Similar marketing does not mean similar proof.
| CJC-1295 Research Use Only | Somatropin (recombinant hGH) FDA Approved | |
|---|---|---|
| Evidence rating |
2/5 Limited
Evidence rating 2 out of 5: Limited
|
5/5 Very strong
Evidence rating 5 out of 5: Very strong
|
| Regulatory status | Investigational; clinical development discontinued. Not approved. Widely sold grey-market. | FDA-approved for growth hormone deficiency, Turner syndrome, Prader-Willi syndrome, short bowel syndrome and several other indications. Distribution for anti-aging use is specifically prohibited by US federal law. |
| Category | Growth Hormone Axis | Growth Hormone Axis |
| Drug class | GHRH analog; the DAC version bears a maleimide linker that binds serum albumin | 191-amino-acid recombinant human growth hormone — a protein, not a short peptide |
| Route | Subcutaneous (research) | Subcutaneous, daily (or weekly for long-acting analogs) |
| Half-life | CJC-1295 with DAC: 5.8–8.1 days in healthy adults, once bound to albumin. CJC-1295 without DAC (modified GRF(1-29)): minutes — no human half-life has ever been published for it, and the figure usually quoted is inferred from sermorelin and native GRF(1-29). | ~3–4 hours subcutaneously |
| Sequence length | 30 residues | 191 residues (protein) |
| Molecular weight | 3,647.3 Da | 22,124.8 Da |
| Studied in | CJC-1295 with DAC: two randomised, double-blind, placebo-controlled ascending-dose trials in healthy adults running 28 and 49 days, measuring GH, IGF-1 and drug pharmacokinetics, plus one overnight GH-pulsatility study. One phase 2 efficacy trial — 12 weeks, multicentre, randomised, double-blind, placebo-controlled, in HIV-associated visceral adiposity — was terminated in July 2006 with no results posted or published, and it is the only CJC-1295 study ever entered on ClinicalTrials.gov. The peptide sold without DAC has no controlled human study at all. | Decades of randomized trials across pediatric and adult deficiency states; large post-marketing safety registries such as KIGS and NordiNet. |
| Who should avoid it |
|
|
| Legal status | Not approved for human use in the US, EU or UK. Sale for human consumption is unlawful. | Prescription drug. US federal law (21 U.S.C. § 333(e)) prohibits distribution for any use other than approved indications, making anti-aging distribution a criminal offence. |
Benefits — CJC-1295
- Sustained GH and IGF-1 elevation
Phase 1 data showed multi-day increases in GH and IGF-1 after a single DAC dose — the pharmacology works as designed.
- Reduced injection frequency
The DAC version requires weekly rather than daily dosing.
- Synergy with ghrelin agonists
Combining a GHRH analog with a GHRP produces a larger GH pulse than either alone — well established in pituitary physiology.
- GH pulsatility survives continuous stimulation
Healthy young men sampled every 20 minutes across an overnight period, before and one week after a single injection of the DAC version, showed unchanged GH pulse frequency and amplitude while trough GH rose about seven-fold; mean GH rose 46% and IGF-1 45%. Unlike injected growth hormone, the rise stays pituitary-mediated rather than replacing pituitary output. One small single-dose study, one lab.
- The response appears to plateau rather than climb
In that same study the two doses compared produced no different GH or IGF-1 response, and the IGF-1 rise correlated with no measured parameter of GH secretion — consistent with a ceiling set by somatotroph capacity rather than by how much drug arrives. Never confirmed in a larger study.
Benefits — Somatropin (recombinant hGH)
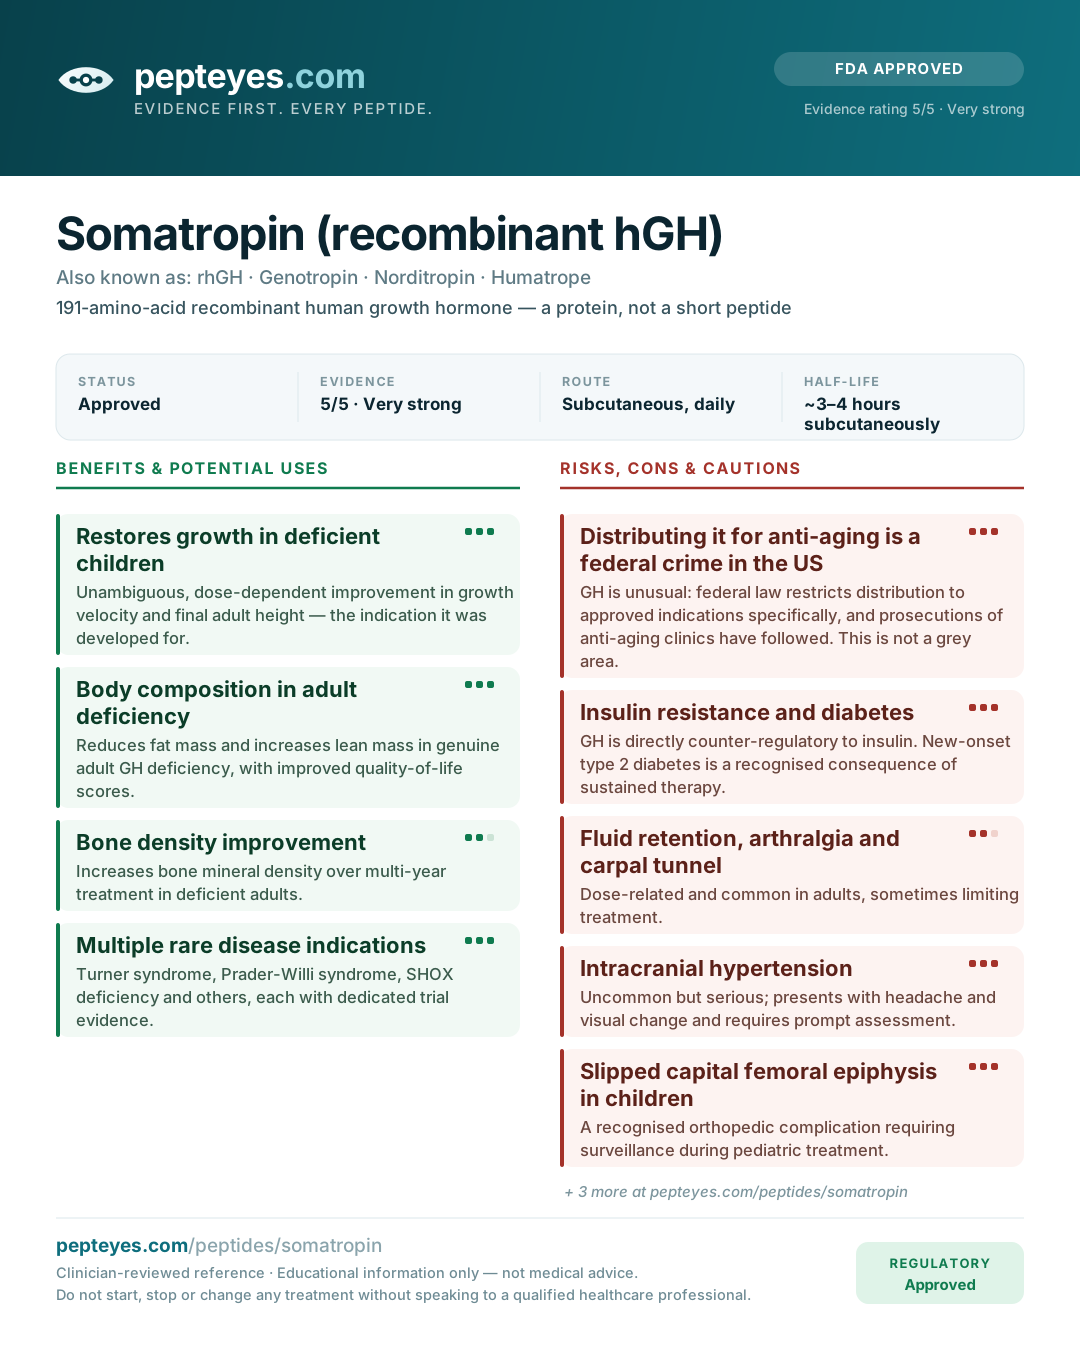
- Restores growth in deficient children
Unambiguous, dose-dependent improvement in growth velocity and final adult height — the indication it was developed for.
- Body composition in adult deficiency
Reduces fat mass and increases lean mass in genuine adult GH deficiency, with improved quality-of-life scores.
- Bone density improvement
Increases bone mineral density over multi-year treatment in deficient adults.
- Multiple rare disease indications
Turner syndrome, Prader-Willi syndrome, SHOX deficiency and others, each with dedicated trial evidence.
Risks & cons — CJC-1295
- Continuous GH exposure is non-physiological
Natural GH is pulsatile. Chronic flat elevation is the pattern seen in acromegaly, and its long-term consequences with this drug are untested.
- Development discontinued
The sponsor stopped work; no phase 2 or 3 efficacy or safety data exist.
- Insulin resistance and glucose elevation
Expected with sustained GH/IGF-1 elevation.
- Fluid retention, paraesthesia, carpal tunnel
GH-excess symptoms reported by users.
- Theoretical cancer promotion
IGF-1 is mitogenic; chronic elevation in people with occult neoplasia is a genuine unknown.
Risks & cons — Somatropin (recombinant hGH)
- Distributing it for anti-aging is a federal crime in the US
GH is unusual: federal law restricts distribution to approved indications specifically, and prosecutions of anti-aging clinics have followed. This is not a grey area.
- Insulin resistance and diabetes
GH is directly counter-regulatory to insulin. New-onset type 2 diabetes is a recognised consequence of sustained therapy.
- Fluid retention, arthralgia and carpal tunnel
Dose-related and common in adults, sometimes limiting treatment.
- Intracranial hypertension
Uncommon but serious; presents with headache and visual change and requires prompt assessment.
- Slipped capital femoral epiphysis in children
A recognised orthopedic complication requiring surveillance during pediatric treatment.

A comparison is not a recommendation. Neither column is being suggested for you. Which — if either — is appropriate depends on your diagnosis, history and medications, and that is a conversation for a qualified clinician.